-

PP405 Is Getting Closer — Protect Your Follicles Before That Day Comes
Once a laboratory idea, “waking dormant hair follicles” has now moved through human trials and toward the next stage of development. But the more interesting question raised by PP405 is bigger than a single drug: What, exactly, remains beneath the hair we think we have lost? And while that future moves closer, what can we do today?
To someone with a full head of hair, a single strand means almost nothing. A few hairs in the shower drain are easily ignored, and a strand on the pillow is simply brushed away.
But once hair loss begins, the value of a single strand changes.
You shift your part from one side to the other in front of the mirror. You wonder whether your forehead looks slightly wider than it did yesterday. After a shower, you may even catch yourself counting the hairs left between your fingers. What was once disposable suddenly becomes something worth protecting.
For decades, hair-loss treatment has largely asked familiar questions: How can we slow the shedding? How can we keep the hair that remains thicker, longer?
Then scientists began looking more closely at the skin where hair had disappeared, and the question changed.
Because something appeared to be left behind.
The hair was gone. The stem cells were still there.
In 2011, researchers compared bald and non-bald scalp from men with androgenetic alopecia. They found that a population associated with hair-follicle stem cells remained even in bald scalp, while progenitor-cell populations involved in the next stages of hair production were markedly diminished. Read the original 2011 JCI study
The finding subtly changed the way hair loss could be imagined. At least in some androgenetic alopecia, the problem might not be that every regenerative component has vanished. Some stem cells may remain while failing to move efficiently into the next stage.
Is losing the hair the same thing as losing all biological capacity to make hair again?
A factory that has been demolished is very different from a factory whose production line has stopped. That does not mean every bald follicle is an intact factory waiting for someone to flip a switch. Some may have weakened after years of miniaturization; others may have undergone structural or environmental changes.
But the possibility was suddenly there:
perhaps the factory had not entirely disappeared.
The next question followed naturally.
Could it be restarted?
That question eventually led to PP405
In 2017, UCLA researchers focused on how hair-follicle stem cells use energy. In mouse studies, altering cellular metabolism influenced the activation of dormant hair-follicle stem cells and the hair cycle. One important target that emerged was the mitochondrial pyruvate carrier, or MPC. Read the original Nature Cell Biology study
This suggested a different approach to hair loss: rather than creating hair from the outside, perhaps medicine could reactivate cells that remain inside the follicle but have gone quiet.
PP405 emerged from that scientific lineage. It is an investigational topical small molecule designed to inhibit MPC and alter the metabolic state of hair-follicle stem cells, with the goal of encouraging dormant follicles to re-enter the growth cycle.
PP405 is not FDA-approved. But the idea is no longer confined to mice or laboratory speculation.
It has been tested in humans.
Then came the number: 31%
The Phase 2a study enrolled 78 men and women with androgenetic alopecia. Participants received PP405 0.05% topical gel or vehicle once daily, with 28 days of blinded treatment in the randomized portion. ClinicalTrials.gov lists the study as completed. View the official Phase 2a record — NCT06393452
The exploratory efficacy signal that attracted the most attention appeared among men with a higher degree of hair loss. At Week 8, 31% of PP405-treated men in that subgroup showed a greater than 20% increase in hair density, compared with 0% in the placebo group. Treatment itself had lasted four weeks, meaning the Week 8 observation came four weeks after dosing stopped.
That number needs to be read carefully.
It does not mean that 31% of all 78 participants regrew hair. It came from an exploratory analysis of a male subgroup with a higher degree of hair loss; the publicly available materials do not provide a denominator that allows the 31% to be converted into a count of the entire study population.
Once that limitation is acknowledged, however, a more interesting question appears.
In science, sometimes the people who do not respond can tell us as much as the people who do. If 31% showed a signal of possibility, perhaps the rest point toward the next question research needs to answer.
Why did some respond while others did not?
What if we are calling different biological states by the same name: “hair loss”?
Two people can appear equally bald. But does that mean the follicles beneath their skin are biologically identical?
One person may have follicles that are largely dormant. Another may have follicles weakened by years of miniaturization. In another, stem cells may remain while the surrounding environment has undergone inflammatory, fibrotic or other changes.
Two scalps can look equally bare while retaining very different capacities for recovery beneath the surface.
That leads to a useful way of framing the question.
‘Regenerative Reserve’
Medicine does not currently have a standard clinical measure for the amount of recoverable potential remaining in a person’s hair follicles.
But when these scattered findings are placed side by side, an intriguing question emerges:
Is the visible degree of hair loss really the same thing as the regenerative potential remaining beneath the skin?
For the purposes of this article, TENVER calls that possibility “Regenerative Reserve.”
Regenerative Reserve is not an established diagnosis, biomarker or clinical scale in hair-loss medicine. It is an analytical concept proposed by TENVER in this article to frame a question emerging across multiple lines of research.
Viewed this way, the 31% becomes more interesting. The future question may not simply be, “Does PP405 work?” It may also become: Which biological state of the follicle is most likely to respond — and could we someday know that before treatment begins?
Hair-loss medicine might eventually expand its question from “How much hair have you lost?” to:
“How much can still be recovered?”
There is reason for caution. A 2024 study using a different MPC inhibitor, UK-5099, in ex vivo human hair follicles found proliferative arrest rather than stem-cell activation. That study did not test PP405, and the compound, dose and experimental context were different, so it does not invalidate PP405’s clinical findings. But it reminds us that human follicle biology is unlikely to obey a simple rule that “MPC inhibition wakes dormant follicles.” Read the 2024 human-follicle study
Perhaps that is precisely why the 31% matters.
The next question may be not only whether a drug works, but for whom — and in what kind of follicle — it works.
TENVER VIEW
PP405 may ultimately succeed, fail, or find its place somewhere between those extremes. But its larger significance may already be visible.
For decades, hair-loss medicine has largely measured what is disappearing: hair count, density, diameter and the expanding area of loss. Regenerative approaches introduce a different question:
What biological capacity remains after the visible hair is gone?
TENVER’s idea of Regenerative Reserve grows from that distinction.
The concept is not a clinical test, and there is currently no validated way to assign someone a “regenerative reserve score.” But if future research can identify why one apparently dormant follicle responds while another does not, hair-loss treatment may eventually become less about classifying how bald someone is and more about identifying what remains biologically recoverable.
That would be a very different way of looking at baldness.

How close is PP405?
PP405 has already moved through Phase 1 and completed its Phase 2a study. According to ClinicalTrials.gov, the study enrolled 78 participants and was completed on October 1, 2025. That same month, Pelage Pharmaceuticals announced $120 million in Series B financing to support the next stage of PP405’s development.
Since then, the company has continued preparing for late-stage trials. In February 2026, Pelage expanded its executive and clinical-operations leadership, saying the changes were intended to support upcoming late-stage trials and that it planned to advance PP405 into late-stage clinical development during the year. In March, the company again stated that it expected to initiate late-stage studies in 2026.
But there is an important distinction between preparing for Phase 3 and actually beginning it. As of late August 2026, the publicly available ClinicalTrials.gov record for PP405 still shows the completed Phase 2a study; a Phase 3 PP405 trial is not yet publicly confirmed there as underway. The most accurate description of PP405’s position today, then, is this:
It has moved beyond early human testing and reached the threshold of late-stage development — but it would be premature to say that it has already crossed that threshold.
The size of the investment does not prove efficacy. Nor would entering Phase 3 guarantee eventual FDA approval. There are still important clinical and regulatory hurdles ahead.
But the opposite exaggeration should also be avoided. PP405 is no longer a speculative technology imagined for some distant generation.
It has already been tested in humans, completed Phase 2a, and is being prepared for large, late-stage clinical testing.
This brings to mind something that seems, at first, completely unrelated.
Some people choose cryonic preservation after death, entrusting their bodies to a future medicine that does not yet exist, hoping science might someday become capable of reviving them. No one knows when — or whether — that future will arrive.
For people losing their hair, fortunately, PP405 is not that kind of distant future.
There are still clinical and regulatory hurdles ahead, but this is no longer merely an idea waiting for another generation of science.
That changes the meaning of waiting.
Instead of simply waiting for the future to arrive, we can ask:
What should we preserve until that day comes?
At this point, the PP405 story leaves the laboratory.
It becomes a story about our own hair.It becomes a story about our own hair.
So what should I do until then?
Articles about experimental hair-loss drugs often end here: more trials are needed; approval will take time.
For someone whose hair is thinning today, that is not enough. Clinical research moves in years.
The hair in the mirror is changing now.
What we can do today is surprisingly unglamorous: avoid unnecessarily losing what we still have.
The first step is not adding something new. It is understanding what you are losing, and why.
If hair loss is progressing, make sure the diagnosis is actually androgenetic alopecia. Sudden shedding, sharply localized loss, scalp pain, redness, severe itching or scaling can point toward other causes. Hair loss has many causes, and finding the cause matters. AAD — Hair-loss diagnosis and treatment
If it is androgenetic alopecia, the next question becomes practical:
Can we slow the clock on follicles that are miniaturizing now?
Existing treatments still matter. Topical minoxidil is widely used for pattern hair loss, and finasteride is an FDA-approved option for male pattern hair loss. They do not work equally for everyone, and suitability, risks and side effects should be discussed with an appropriate clinician.
The important point is not to choose between PP405 and today’s therapies. Existing treatments are not obsolete drugs competing with a future regenerative treatment. Slowing miniaturization today and potentially reactivating dormant follicles tomorrow may address different moments in the same long process.
There is no clinical evidence that minoxidil or finasteride preserves a person’s future responsiveness to PP405. That line should be clear.
But there is equally little sense in allowing treatable hair loss to progress untreated for years simply because a more exciting therapy may be coming.
Before adding more, find out what is actually missing
I once bought a hair-loss supplement after reading a persuasive advertisement. The ingredients sounded almost indispensable for healthy hair.
Then the bottle arrived, and I looked carefully at the label.
I had to laugh.
Most of the ingredients being promoted for hair were already in the multivitamin I was taking.
That experience illustrates an important distinction:
A nutrient being necessary to make hair is not the same as more of that nutrient making more hair.
A car factory needs steel. But doubling the steel piled in the warehouse does not double the number of cars coming off the line. If production has stopped for another reason, what matters is not more steel.
It is finding out why the line stopped.
Hair deserves the same logic.
Inadequate protein or calories and deficiencies in nutrients such as iron can contribute to hair loss. If diet, symptoms or medical history suggest a deficiency, appropriate evaluation and correction make sense. But taking increasing amounts of nutrients simply because they are marketed for hair is a different proposition. The American Academy of Dermatology also notes that excessive intake of some nutrients, including selenium and vitamins A and E, has been linked to hair loss. AAD — Hair-loss management and nutrition guidance
The principle is simple:
Replace what is missing. Don’t keep adding what is already sufficient.
Extreme calorie restriction belongs in the same conversation. If the entire body is deprived of adequate energy and protein, hair can pay part of the price.
Take care of the place where the follicle lives
Hair follicles do not live in a vacuum.
Persistent dandruff, seborrheic dermatitis, severe itching or scalp inflammation should not simply be ignored. Treating those conditions does not cure androgenetic alopecia, but there is no reason to leave treatable scalp disease unmanaged while thinking about the future health of the follicle.
Preventable physical damage matters too. Hairstyles that repeatedly pull on the hair can cause traction alopecia and, when prolonged, may eventually lead to permanent loss. Repeated high heat, harsh chemical processing and rough handling can add unnecessary damage to already fragile hair. AAD — Traction alopecia and damaging hairstyles
That does not mean every scalp massage, special shampoo or oil should be promoted into a regenerative treatment. Something that feels pleasant or improves hair care is not automatically something that slows androgenetic alopecia or preserves future PP405 responsiveness.
The more useful question may be:
Before asking “What else can I add for my follicles?” ask “What damage can I stop imposing on them?”
Don’t turn your scalp into a laboratory out of impatience
Whenever an experimental drug attracts attention, products claiming a “similar ingredient,” “same pathway” or “research-grade” alternative tend to follow.
PP405 remains an investigational drug. There is no validated over-the-counter equivalent of PP405, and buying research compounds or MPC inhibitors online to experiment on your own scalp is not a sensible way to prepare for future medicine.
As the MPC research itself demonstrates, touching the same biological pathway does not make two compounds equivalent.
Acting on the same pathway is not the same thing as being the same drug.
For people interested in future PP405 studies, official trial information is the better route: ClinicalTrials.gov — NCT06393452 and Pelage PP405 trial information.
And then document it — photographs are not treatment; they are the dashboard
Take standardized photographs every three to six months: same lighting, same distance, same angles, including the hairline and crown.
But do not confuse photographs with doing something for the follicle.
Photographs are not treatment. They are the dashboard.
They can help show whether the strategy you chose appears to be working or whether the diagnosis or treatment deserves another look. The eye that sees the mirror every morning is remarkably poor at detecting gradual change. Two photographs taken months apart under the same conditions can be much less forgiving.
So photographs come after action.
First do what can reasonably be done.
Then measure what is happening.
Take your follicles with you until that day
For years, the hair-loss market has told us to add something: another shampoo, another supplement, another ingredient, another promise that this time it will be different.
Following the PP405 story to its logical end leads somewhere else.
If regenerative medicine really does move toward reactivating biological capacity that remains inside the follicle, our job today is not to imitate tomorrow’s medicine. It is to treat what can be treated, correct what can be corrected, and preserve what we still have for as long as reasonably possible.
None of today’s treatments or habits guarantees a future response to PP405.
But uncertainty is not the same thing as helplessness.
We are not simply waiting for PP405. We are taking our follicles with us until that day.
And for the person who began this story shifting a hair part from one side to the other in front of a mirror, this long scientific journey eventually returns to something very small.
One strand.
And beneath that strand, a possibility that may still be alive.When the not-too-distant future arrives, having as much as possible left for medicine to treat — that may be the most realistic preparation we can make today.
PP405 is a story about the future. Your follicles are a problem of today.
Sources
- Garza et al., Journal of Clinical Investigation (2011) — Hair-follicle stem cells in bald scalp
- Flores et al., Nature Cell Biology (2017) — Lactate metabolism and HFSC activation
- ClinicalTrials.gov — PP405 Phase 2a, NCT06393452
- Pelage Pharmaceuticals — Publications & Press
- Pelage — AAD 2026 PP405 update and planned late-stage studies
- Pye et al., PLOS ONE (2024) — MPC inhibition in human hair follicles
- American Academy of Dermatology — Hair-loss management guidance
Related TENVER: What If Baldness Isn’t Permanent?
-

Why Can’t We Just Become Friends by Chance Anymore?
We still encounter countless people. What may have changed is not how many people we meet, but how long they remain in our lives before a stranger has the chance to become someone.
In the 1953 film Roman Holiday, Princess Ann does not set out to meet Joe Bradley. Escaping the suffocating formality of royal life, she slips into the streets of Rome, where the effects of a sedative eventually leave her asleep in public. Joe, an American reporter passing by, finds her without realizing that the young woman in front of him is a princess.
Had they simply crossed paths and continued in opposite directions, there would have been no story. But one accident leads to another encounter, and the two begin moving through Rome together—walking, talking, laughing, accumulating the small memories through which a stranger gradually becomes a particular person.
Cinema makes such encounters beautiful, but the beginnings of many real relationships are not so different. We became friends with someone because we happened to be assigned to the same classroom, hired by the same company, raised in the same neighborhood, seated at the same table through mutual friends, or drawn repeatedly to the same church, park, café or corner store. At the time, none of these circumstances seemed especially consequential. One encounter simply followed another until conversation accumulated into familiarity, familiarity into memory, and eventually a person who had once meant nothing in particular acquired a name in our lives: friend.
We usually describe such relationships by saying that the friendship “just happened.”
But did it?
Perhaps what felt natural was not that friendship emerged from nowhere, but that society was quietly arranging so much of the encounter for us that we barely noticed the arrangement. Schools placed the same people in the same rooms day after day. Workplaces brought unrelated lives together for hours at a time. Neighborhoods, churches, parks, markets, cafés and local businesses created environments in which yesterday’s face could become today’s face and then tomorrow’s face again. We still chose whom to trust, whom to like and whom to love, but we did not have to choose from scratch whom we would have the chance to see again.
Perhaps friendship was never quite as effortless as we remember.
Society was doing more of the arranging than we realized.
Meeting Someone Is Not the Same as Forming a Relationship
The Korean thinker Shin Young-bok once used a striking image to describe a certain kind of modern human encounter: the meeting of billiard balls. Two balls certainly meet. They make contact, sometimes forcefully, but at the very moment of contact they are propelled away from each other along separate trajectories. There has been an encounter, but nothing accumulates between them.
The metaphor may be even more revealing today because we are, in one sense, surrounded by more human connection than almost any generation before us. Our phones contain hundreds of contacts. Social media allows us to know where people we have never met went on vacation, what they ate and when they celebrated a birthday. On a subway in a large city, dozens of strangers may stand inches apart while remaining almost entirely absent from one another’s lives.
Recent data suggest that the story is therefore more complicated than the familiar claim that modern people simply “have no friends.” In a 2025 Pew Research Center survey, 81 percent of American adults said they had at least one close friend outside their family, and people with close friends often communicated with them frequently through text, social media, phone or video. Yet only 29 percent said they saw a close friend in person at least a few times a week. We may not simply be becoming disconnected; we may be becoming connected differently.
That raises a more interesting question. Among the thousands of people who pass through our lives, why do some remain strangers while a few become friends?
One answer offered by social science is almost embarrassingly simple: we see them again.
In a 2021 randomized experiment involving 2,966 students across 182 classrooms, researchers found that sitting next to another student increased the predicted probability of a mutual friendship from 15.3 percent to 22.3 percent. Children in classrooms are not adults navigating modern social life, so the finding should not be stretched beyond what it shows. But it offers unusually clean evidence for something researchers have long observed: physical proximity and repeated encounter can alter the probability that a relationship begins.
Our own experience makes the mechanism easy to recognize. Someone we see once is a stranger; seen again, that person becomes “the person I saw yesterday.” Another encounter turns a stranger into a familiar face. Eventually there may be a name, then a greeting, then a conversation, and somewhere along that progression a quiet but consequential transformation takes place.
A stranger becomes someone.
Friendship may only become possible after that.
Before We Care, We Have to See
More than two thousand years ago, the Chinese philosopher Mencius recorded a scene that had nothing to do with friendship and yet captures something subtle about the way human feeling begins.
King Xuan of Qi sees an ox being led away to be sacrificed in a ritual. Watching the frightened animal, the king cannot bear what he sees and orders that the ox be spared and a sheep substituted in its place. The obvious objection follows: if the ox deserves compassion, why not the sheep?
Mencius is interested not simply in the inconsistency but in what caused the king’s compassion to awaken. The king had seen the ox; he had not seen the sheep.
The original argument is political and moral. Mencius wants the king to extend the compassion he feels toward the animal before him to people beyond his immediate sight. But embedded in the story is an observation about the human heart that remains recognizable more than two millennia later: abstract existence does not move us as readily as particular presence does. Something changes when a being enters our field of attention and ceases to be one among many.
Millions of people may live in our city, and billions may be theoretically reachable through a screen, but most remain abstractions. Then there is the person who appears every Saturday morning at the same café. The neighbor we repeatedly meet in the elevator. The person who runs at roughly the same pace beside us every Tuesday evening.
Eventually the face acquires a name, the name acquires memories, and the memories begin to carry a small amount of concern. One morning the familiar person is absent, and for the first time we notice the absence.
Perhaps relationships begin slightly earlier than we think—not with the exchange of phone numbers, not even with the first real conversation, but when one human being begins to become visible to another.
Seen this way, several seemingly unrelated changes in modern life begin to look like parts of the same story.
Convenience Removed More Than Inconvenience
One of the great projects of modern life has been the removal of friction. We can bank without entering a bank, shop without entering a store and eat restaurant food without entering a restaurant. Entertainment comes to the living room, meetings appear on screens, and for many kinds of work it is now possible to complete an entire productive day without going to an office at all.
Much of this is genuine progress. The time recovered from commuting is real. The flexibility of remote work can be enormously valuable, especially for people balancing work with children, caregiving, disability or geographic constraints. There is little reason to romanticize standing in lines, sitting in traffic or performing errands that technology can accomplish more efficiently.
But we are very good at calculating what convenience saves and much less practiced at calculating what used to occupy the space we saved.
We can measure the minutes no longer spent commuting, shopping or waiting for lunch. It is harder to measure the familiar faces that once inhabited those minutes: the person encountered on the morning train, the colleague who appeared in the same lunch place, the neighbor seen at a local shop, the barista who eventually knew an order without being told.
Most of those encounters led nowhere. Riding the same train did not automatically produce friendship, nor did buying coffee from the same place.
But that is precisely the point.
Relationships emerge from a vast number of encounters in which, most of the time, nothing happens. Only a tiny fraction continue long enough for something to happen.
It would therefore be far too simple to claim that delivery apps, online shopping or remote work have caused loneliness. Even recent research finding higher adjusted odds of loneliness among people working remotely three or more days a week is observational and cannot establish that remote work itself is the cause. The more interesting question lies underneath the argument over whether remote work is good or bad:
When we removed friction from everyday life, did we inadvertently remove some of the coincidence as well?
That question does not require us to restore the inconvenience. It asks whether we can preserve the freedom modern life has given us while recreating, in new forms, some of the human conditions that used to accompany it.
And one important kind of relationship has already begun doing exactly that.
Love Found a New Intermediary
For much of modern history, romantic relationships also depended heavily on existing social networks. Friends introduced friends. Families made introductions. Schools, workplaces, neighborhoods and religious communities repeatedly placed strangers within reach of one another.
As those traditional pathways weakened, however, romantic life did not simply wait for coincidence to return. Technology entered the space.
Research by Stanford sociologist Michael Rosenfeld and colleagues found that, among heterosexual couples in the United States, meeting online overtook meeting through friends around 2013. Their paper described the internet as “disintermediating” friends and family—the traditional intermediaries who once connected potential partners.
But there is another way to describe what happened.
Technology removed an intermediary and then became the intermediary.
When love could no longer rely as heavily on coincidence, we built new infrastructure for meeting. Among partnered Americans under 30 surveyed by Pew, one in five said they had met their current spouse or partner through a dating site or app.
Now place friendship beside romantic love and a curious cultural difference appears.
Saying “I’m looking for a partner” sounds perfectly ordinary. So does looking for a job, a home or almost anything else of lasting importance. Yet saying “I’m looking for a friend” carries a strangely different emotional weight. It can sound lonely, even vaguely embarrassing, as though friendship were one important thing in adult life that we should never appear to be searching for.
Perhaps friendship remains one of the few relationships we still expect to arrive without our appearing to look for it.
There may be a familiar cultural lag at work here. As we explored in “Why Does Adulthood Feel So Expensive?”, the conditions of modern life can change faster than the expectations we use to judge them. Something similar may be happening with relationships: the ways people meet are changing faster than our ideas about what a “natural” meeting is supposed to look like.
But if the social conditions that once produced accidental friendship are changing, why should intentionally creating opportunities for friendship be considered artificial?

Perhaps We Have to Create the Conditions for Chance
There are signs that some people are already experimenting with an answer. Running clubs, book groups, hiking communities, craft circles and other recurring in-person gatherings have become prominent enough among younger adults that the phrase “community-maxxing” has recently been used to describe the search for more intentional offline social life. It is too early to declare this a broad social transformation, but it is an intriguing cultural signal: people may not be rejecting digital life so much as looking again for places where the same human beings can repeatedly appear in front of one another.
At first, deliberately going somewhere in the hope of an accidental friendship sounds almost contradictory.
But was the past really so different?
A school friendship feels natural, yet someone designed the school, divided the grades, assigned the classroom and created the timetable that repeatedly put those two children together. A friendship at work may feel equally spontaneous, although an organization hired both people and brought them into the same place five days a week.
The real difference, then, may not be whether encounters are arranged.
It may be who does the arranging.
In the past, institutions quietly arranged much of our repeated proximity for us. Increasingly, we may have to arrange some of it ourselves.
That does not require surrendering the freedom modern life has created. Someone who can work remotely does not need to return to the office five days a week simply to prove that human contact matters. But perhaps there is value in choosing one or two days to go in—not merely to occupy a desk, but to be there on days when the same colleagues are there, to have lunch with them, to become part of one another’s ordinary weeks.
A person working from home might choose to spend one afternoon each week in the same neighborhood café or coworking space. Someone who exercises alone because it is more efficient might reserve one evening for a recurring running group. A household that can have virtually everything delivered might still walk to the neighborhood market occasionally, not because shopping in person is technologically superior, but because a neighborhood only becomes socially meaningful when people repeatedly appear in it.
None of these acts guarantees friendship, and that is important. Their purpose is not to manufacture relationships but to restore some of the conditions from which relationships can emerge.
Remote work illustrates the distinction particularly well. If eliminating a commute returns an hour or two to someone’s day, there is no reason that time must be handed back to the employer. But perhaps some of it can be handed back to people—to an old friend, a regular gathering, a neighborhood café, a recurring class, or simply a place where familiar faces have the opportunity to become more familiar.
Convenience gave us time back. The question now is where we choose to reinvest some of it.
The same principle applies beyond individual choices. For employers concerned about social cohesion, the more useful question may not be simply how many days workers come to the office, but whether the same people are there at the same time often enough for relationships to accumulate. A company where everyone comes in twice a week on unrelated days may satisfy an attendance policy while recreating very little repeated proximity.
Cities and communities might ask a similar question. A successful public space need not merely attract large numbers of people once; perhaps it should give the same people reasons to return. A successful community might measure not only how many attended an event but how many encountered one another again. And technology designed for social connection might eventually be judged not only by how many introductions it produces, but by whether those introductions have any realistic opportunity to become relationships.
The challenge, then, is not to choose between freedom and connection.
It is to ask a better question:
How do we restore repetition without surrendering freedom?
The answer does not have to begin with a major social program. It can begin with something much smaller: allowing ourselves to admit that we would like more friendship, choosing occasionally to do with others what could more efficiently be done alone, or returning to the same place at the same time rather than continually optimizing for novelty and convenience.
What matters is not maximizing the number of people we meet.
It is preserving in our lives the possibility of meeting the same people again.
And this may also require us to reconsider what we mean when we call a relationship “natural.” A friendship formed in a running club is not artificial because someone joined the club hoping to meet people, any more than a marriage is less real because the couple first met through an app.
Perhaps a natural relationship is not one whose beginning was accidental.
It is one whose feelings were not forced after the beginning.
We can design a place to meet. We can recommend people to one another. We can even increase the likelihood that the same people will meet repeatedly. What no institution or algorithm can determine is why we eventually notice when one particular person fails to appear, why we begin wanting to tell that person something that happened during our day, or why, among thousands of human beings, that person’s happiness or sorrow gradually begins to matter to us.
That final distance still has to be crossed by human beings themselves.
Why Can’t We Just Become Friends by Chance Anymore?
Perhaps, then, we have not forgotten how to make friends. What may be disappearing is some of the time and space through which a potential friend moves from stranger to familiar face, from familiar face to a person with a name, and eventually from a name to someone who matters.
Princess Ann and Joe Bradley meet by accident in Roman Holiday, but the reason their encounter has remained memorable for generations is not simply that two strangers happened to cross paths on a street in Rome. The accident continued. They spent time together, and during that time each ceased to be merely another person in the world and became a particular person to the other.
Real friendship may not be so different.
Every day we collide with other lives, sometimes like Shin Young-bok’s billiard balls, touching briefly before continuing along separate trajectories. But occasionally one encounter becomes a second, a face acquires a name, the name gathers memories, and eventually there comes a day when that person does not appear and we notice the absence.
Somewhere in that long and almost invisible progression, an encounter becomes a relationship.
What modern life may be short of, therefore, is not people. We already see and communicate with extraordinary numbers of them. What may be growing scarce is something quieter: enough repetition, enough time and enough shared presence for one human being to become someone to another.
In the past, much of that human coincidence was supplied by the structure of everyday life. If less of it arrives automatically now, perhaps we should not simply wait for it to return.
We can make room for it.
TENVER VIEW
For a long time, we have assumed that friendship should happen naturally. Yet many of the friendships we remember as spontaneous were nurtured by an invisible architecture of schools, workplaces, neighborhoods and communities that repeatedly brought the same strangers into one another’s lives.
If that architecture is changing, deliberately seeking friendship may not be what is unnatural. What may be outdated is our expectation that friendship should still appear effortlessly under conditions that no longer produce as many repeated encounters.
We do not need to reverse modern life to respond. There is no reason to surrender the freedom of remote work, abandon online convenience or manufacture unnecessary inconvenience. We can instead use a small part of the freedom we have gained to recreate some of the repetition we have lost—going into the office occasionally when the same colleagues will be there, returning to the same café, joining the same group at the same time each week, or simply leaving room in an optimized life for familiar faces to appear again.
The point is not to meet more people.
It is to give some of the people we meet a chance to stop being strangers.
We cannot manufacture friendship, but we can create more of the conditions in which friendship becomes possible. Perhaps that is one of the small human tasks of a more convenient age: to restore repetition without surrendering freedom, and to give one another enough time to become someone.
That may be where the next friendship begins.
Sources
Pew Research Center. “Where Men and Women Turn for Emotional Support and Social Connection.” January 16, 2025.
Pew Research Center — Social Connection and Close FriendsRohrer, Julia M., Tamás Keller, and Felix Elwert. “Proximity Can Induce Diverse Friendships: A Large Randomized Classroom Experiment.” PLOS ONE, Vol. 16, No. 8, 2021.
PLOS ONE — Proximity Can Induce Diverse FriendshipsRosenfeld, Michael J., Reuben J. Thomas, and Sonia Hausen. “Disintermediating Your Friends: How Online Dating in the United States Displaces Other Ways of Meeting.” Proceedings of the National Academy of Sciences (PNAS), Vol. 116, No. 36, 2019.
PNAS / PubMed Central — Disintermediating Your FriendsMcClain, Colleen, and Risa Gelles-Watnick. “From Looking for Love to Swiping the Field: Online Dating in the U.S.” Pew Research Center, February 2, 2023.
Pew Research Center — Online Dating in the U.S.“Remote Work and Loneliness: Evidence from a Nationally Representative Sample of Employed U.S. Adults.” Journal of Affective Disorders, 2026. Based on data from 87,317 respondents in the 2024 U.S. Household Pulse Survey.
PubMed — Remote Work and LonelinessMencius. King Hui of Liang, Part I — the account of King Xuan of Qi, the ox and the sheep (“You saw the ox, and had not seen the sheep”). Chinese Text Project.
Chinese Text Project — Mencius, King Hui of LiangThe Guardian. “‘Community-maxxing’: Gen Z Are Done with Doomscrolling — and Ready to Socialise.” August 25, 2026.
The Guardian — Community-maxxingShin Young-bok. “Classic Lectures: Mencius.” Pressian, February 15, 2002. Shin discusses modern human relationships through his metaphor of “the meeting of billiard balls”—brief points of contact that end before they can develop into lasting relationships. The idea was later developed in his book Gangui: Naui Dongyang Gojeon Dokbeop, Dolbegae, 2004.
Pressian — Shin Young-bok’s Classic Lectures -

Why Does Adulthood Feel So Expensive?
Buying a home, moving out, getting married, having children—each seems to be happening later. We often say younger generations simply want different things. But perhaps what changed first was not what they wanted. Perhaps it was the road they were asked to travel.
Imagine someone approaching 30 who still lives with his parents. He graduated from college, has a steady job, contributes to household expenses, and saves part of every paycheck. He is not particularly extravagant, nor is he living entirely at his parents’ expense. Given today’s rents and home prices, staying home for a few more years while building savings may be one of the most rational financial decisions he can make.
And yet, at a family gathering, someone asks:
“You’re still living with your parents?”
The question may be harmless, but it lingers. A friend buys a house. Another posts wedding photos, followed a year or two later by pictures of a new baby. Without meaning to, he begins measuring his life against theirs. He has a job. He is saving. He is planning for the future. And still, a thought creeps in: Why am I still here?
To his parents’ generation, the situation may look even stranger. Many were already married at his age. Some had bought modest homes. Some already had children. And so it becomes easy to say that young adults today are taking longer to grow up.
But is he really late? Or are we measuring his life with an old timetable?
The Road Changed First
For much of modern American life, adulthood was imagined as a fairly familiar sequence: finish school, get a job, leave your parents’ home, get married, buy a house, have children, then begin preparing for retirement.
The past, of course, was never that simple. Earlier generations endured recessions and periods of punishingly high interest rates, while women and racial minorities faced barriers far greater than many do today. It would be historically careless to say that life was easy for previous generations and uniquely difficult for this one.
Still, that sequence became a powerful social benchmark. We learned to judge where someone “should” be by a certain age, and milestones such as living independently, marrying, owning a home and having children became more than personal choices. They became visible evidence that someone had become an adult.
But the timetable of actual life has already moved. In 1975, the median age at first marriage in the United States was 23.5 for men and 21.1 for women. By 2025, it had risen to 30.8 and 28.4. That same year, 58% of Americans ages 18 to 24 and 16% of those ages 25 to 34 were living in their parents’ home.
It is tempting to explain this simply as a change in values, and values certainly have changed. Women have far greater economic independence and choice. Marriage no longer carries the same expectations it once did. Remaining child-free has become a legitimate life choice for many, while others value mobility and flexibility more than homeownership. It would therefore be equally simplistic to assume that young adults want exactly the same lives their parents had but simply cannot afford them.
Place those changing values beside today’s economic conditions, however, and another picture begins to emerge.
Between 2019 and 2024, inflation-adjusted median household income among U.S. households under 40 rose about 9%, while median home values rose roughly 30%. Add higher mortgage rates, and Pew Research Center estimated that typical monthly homeownership costs rose from $1,689 to $2,776—an increase of about 64%. Over the same period, the share of renters under 40 with enough income to afford those monthly ownership costs fell from 56% to 37%.
But the more revealing part of the story is not simply that houses became more expensive. When it takes longer to afford a house, more than the date of a home purchase moves. Someone may stay with parents longer to save for a down payment. Delayed independence may alter marriage plans. High housing costs after marriage may affect when a couple feels ready for children. Student debt, retirement savings, insurance and childcare are all drawing from the same paycheck, which means these decisions can no longer be treated as separate financial events.
That is what gets lost when we simply say, “Everything is more expensive now.” It is not only that the price of one future has gone up. Several different futures are now competing for the same paycheck.
Save more for a house and another form of saving may have to wait. Pay off student loans first and the down payment takes longer. Have a child and housing costs suddenly coexist with childcare costs. Once financial pressure on one stage of life begins changing the timing of the next, money becomes something else.
It becomes time.
And from that point forward, economics alone can no longer explain the story.
When Money Moves Time, Time Begins to Move Culture
Deloitte’s 2026 survey of more than 22,500 Gen Z and millennial respondents across 44 countries found that 55% of Gen Z and 52% of millennials had delayed major life decisions because of financial concerns. Housing affordability and availability also affected career decisions and where to work for 69% of Gen Z and 64% of millennials.
The revealing word here may be not “abandoned,” but “delayed.” Someone may still want a house but conclude that now is not the time. A couple may still want children but decide they need more stability first. A worker may want to change jobs but decide that giving up current security is a risk they cannot yet afford.
Nor does this necessarily describe a generation that has given up on the future. In the same Deloitte survey, 53% of Gen Z and 45% of millennials expected their personal financial situation to improve over the following year. Many appear to be postponing decisions under pressure without abandoning the future they imagine for themselves.
That distinction matters. When one person delays marriage for two years because of housing costs, it remains a private economic decision. When millions make similar decisions, something larger begins to happen. The average age of marriage moves. People remain with parents longer. The timing of homeownership and childbearing shifts. What begins as an adaptation to economic conditions can, if repeated long enough, become an ordinary way of living.
Eventually, we stop calling it economic adaptation. We call it culture.
So when we hear that young people marry later now, or that they care less about owning a house, another question is worth asking. Did values change first and produce new behavior, or did behaviors adopted in response to new economic conditions gradually become part of a new set of values?
Reality is probably moving in both directions. Values have changed, and economic conditions have changed. What matters is that they do not move independently. Economics changes choices; repeated choices change culture; and the culture that emerges begins shaping the choices that follow.
Some of what we casually describe as the personality of a generation may therefore be, at least in part, the imprint of the economic environment that generation encountered.
That raises a more difficult question. If people’s actual lives have adjusted to new conditions, have our expectations of what a normal life should look like changed at the same speed?
It does not appear that they have.
Marriage ages have risen. Living with parents into adulthood has become more common. The economics of buying a home have changed dramatically. In other words, the timetable of actual life has already moved. Yet we still look at a 30-year-old living with parents and ask, “Still?” We still ask unmarried adults when they are finally going to settle down. And young adults themselves, fully aware of today’s economics, can still feel behind when a friend buys a house.
Something important becomes visible here that individual statistics about housing or marriage tend to obscure:
The economic timetable and the cultural timetable are moving at different speeds.

The economic timetable responds relatively quickly to housing prices, wages, employment and education costs. People delay home purchases, remain with parents longer, and adjust marriage or childbearing plans. The cultural timetable is slower. It remains embedded in our parents’ experiences, comparisons with our peers, the families we grew up watching, and old assumptions about where someone “should” be at a certain age.
That makes it possible to live rationally according to today’s economy while judging yourself according to yesterday’s timetable. Staying with parents and saving aggressively may be financially wise, yet still feel like a failure to launch. Delaying marriage may be the right decision for a couple, yet a friend’s wedding can still produce the uncomfortable sensation of being behind.
The gap between economic time and cultural time is then carried not by society as an abstraction, but by individuals as emotion.
The cost of adulthood may not be only financial. It may also be the cost of feeling late.
Housing, rent, tuition and childcare can be measured in dollars. The cost of living rationally in one era while feeling that you have failed the expectations of another does not appear in any economic statistic.
The Paradox of Family
Follow that thought a little further and another paradox appears. We have long associated adulthood with becoming independent from one’s parents, yet as the price of economic independence rises, parental resources may become more important in reaching it.
Someone who can remain at home for several additional years may save money that would otherwise disappear into rent. Parents who can contribute to a down payment may help a child enter the housing market sooner. Grandparents who can provide childcare may make it easier for two parents to remain in the workforce. Research on parental financial transfers and young-adult homeownership has likewise found an association between parental assistance and the transition into homeownership.
This complicates the way we usually think about inequality. Imagine two 30-year-olds who each earn $80,000 a year. One can live with parents for several years and redirect what would have been rent toward a down payment. The other must pay substantial rent throughout those same years. Their incomes are identical, but it is difficult to imagine that their economic positions several years later will necessarily be the same.
Income, in other words, may not be the only difference that matters. There may also be a difference in how long someone can afford to wait.
Years in which someone does not have to rush out of the family home, years in which rent can become savings, or years in which relatives can help with childcare can all create room for the next decision. Seen this way, families may pass something to the next generation besides money and property.
They may also pass down the ability to wait.
There is a peculiar irony in that. In a society that has long treated independence from family as one of the clearest markers of adulthood, achieving independence may increasingly depend on what kind of family support a person has available.
That, in turn, forces us to ask what we have actually been measuring when we call someone an adult. A home, a separate address, marriage, children and a stable career are visible. Responsibility, restraint, judgment and the ability to live with the consequences of one’s choices are much harder to see. Perhaps we have sometimes used visible economic outcomes as proxies for something far more difficult to measure: maturity.
Maturity should not have a price tag. But many of the things we have used as evidence of maturity do—and their prices have changed.
Owning a home, establishing a household and raising a family can remain deeply meaningful goals without requiring us to assume that the age at which someone reaches them is a reliable measure of how fully that person has grown up.
Where Does Delayed Time Go?
There is one more question, and it points forward. If buying a home happens later, and marriage and childbearing move later as well, it is tempting to imagine that the entire course of life simply shifts backward by several years.
But not every clock in life moves together.
Parents continue to age. Fertility has biological constraints. Retirement eventually arrives. Responsibilities delayed in early adulthood may therefore not disappear; some may meet one another later within a narrower stretch of life. A person may be raising children when aging parents begin to need care. A mortgage may coexist with college expenses and the need to accelerate retirement savings.
In a 2025 survey, 54% of Americans in their 40s had both a parent age 65 or older and either a minor child or an adult child they were financially supporting—the group commonly described as the “sandwich generation.” Across all U.S. adults, the figure was 25%.
It would be a mistake to claim that delayed marriage or homeownership caused this. Longer lifespans, support for adult children and many other forces are involved. But the phenomenon raises a question worth watching: are the stages of adult life simply moving later, or are housing, childrearing, eldercare and retirement preparation beginning to compress into a narrower portion of adulthood?
If so, some of the rising cost of adulthood may not be paid only in dollars today. Time postponed earlier in life may return later in the form of overlapping responsibilities. That possibility requires much more study, but it suggests that “young people are doing everything later” may be far too simple a description of what is happening. The structure of time across adult life itself may be changing.
And by this point, our view of the nearly 30-year-old still living with his parents has changed as well. At the beginning, we asked why he had not yet left home. But once his economic circumstances and the future he is preparing for are considered together, the more interesting question may no longer be why he has not yet become an adult.
It may be what, exactly, we mean by adulthood now.
Perhaps younger generations are not simply arriving later at the old destination. As the relationships among money, family, marriage and work change, the destination itself may be moving.
The Old Clock
For a long time, we have looked at a person’s age and used it to judge where that person should be in life. By 30, we imagined independence. Somewhere around there, marriage, a home and children were supposed to begin appearing too.
But what if the road itself has changed?
What if we are demanding the same arrival time from people who are no longer traveling the same distance?
Personal responsibility still matters. Working hard, saving, making choices and accepting their consequences have not become irrelevant.
But before declaring that an entire generation is running late, there is one thing worth checking.
Are they really late—or are we still looking at an old clock?
TENVER VIEW
For generations, we have treated leaving home, marriage, homeownership and children not simply as life events, but as evidence that someone has successfully entered adulthood.
The problem is that the price and timing of those milestones have changed faster than the expectations surrounding them.
Perhaps the question, then, is not whether adulthood still requires responsibility. It does. The question is whether we should continue measuring that responsibility by a timetable built under different economic conditions.
Responsibility and arriving “on time” are not necessarily the same thing.
Sources
U.S. Census Bureau — America’s Families and Living Arrangements: 2025
Median age at first marriage and the share of young adults living in their parental home.Pew Research Center — Buying a Home Has Gotten Harder for Young Adults in Most U.S. Metro Areas
Home prices, household income, mortgage costs and affordability among households headed by adults under 40.Deloitte — 2026 Gen Z and Millennial Survey
A global survey of more than 22,500 Gen Z and millennial respondents across 44 countries, including financial pressures, housing concerns and delayed major life decisions.Harvard Joint Center for Housing Studies — The Role of Parental Financial Assistance in the Transition to Homeownership by Young Adults
Research examining the relationship between parental financial transfers and young adults’ transition into homeownership.Pew Research Center — More Than Half of Americans in Their 40s Are “Sandwiched” Between an Aging Parent and Their Own Children
Data on Americans simultaneously navigating responsibilities involving their children and aging parents.
-

Why Are You Exhausted All Day — But Wide Awake at Night?
New research is revealing why a tired brain can still refuse to sleep — and why retraining it may sometimes matter as much as sedating it.
All day, you are exhausted. Getting out of bed is difficult, and by afternoon you are reaching for coffee. On the way home, you promise yourself that tonight you will finally go to bed early. But when you get into bed, something strange happens: you are no longer sleepy. Tomorrow’s work appears in your head, followed by an unanswered message and perhaps something embarrassing you said years ago.
You check your phone for a minute, and a minute becomes twenty. Then you look at the clock: 1:47 a.m. That is when perhaps the worst thought arrives — “Even if I fall asleep right now, I only have five hours left.” From that moment, you are no longer simply waiting for sleep. You are trying to make it happen, and sleep seems to move even farther away.
How can someone be completely exhausted and still be unable to sleep? The answer may begin with a distinction most of us rarely make: being tired and being ready to sleep are not the same thing.
Young Adults Are Struggling to Fall Asleep
Insomnia is hardly just an older person’s problem. Data released by the U.S. National Center for Health Statistics in April 2026 found that 30.5% of American adults slept less than seven hours per day on average in 2024. More strikingly, 18.3% of adults ages 18 to 34 reported trouble falling asleep most days or every day, compared with 12.8% among adults 65 and older. In that survey, difficulty falling asleep actually declined with age.
That does not mean younger people have worse sleep in every respect. Older adults were more likely to report trouble staying asleep. But the difficulty of simply getting to sleep appears to be particularly common among younger adults. For a generation that carries work, entertainment, relationships, news and social life in a device beside the pillow, the question feels increasingly familiar: why can a young, exhausted body still have a brain that refuses to shut down?
A Tired Body Can Still Have an Alert Brain
Sleep is not simply what happens when the body runs out of energy. The longer we stay awake, the more pressure for sleep generally builds, while our circadian clock helps determine when the brain expects wakefulness and when it expects sleep. Yet researchers studying chronic insomnia increasingly focus on another process: hyperarousal — a state in which the body may be lying still while the brain remains unusually alert.
Worry, planning, replaying conversations, monitoring the clock and wondering whether sleep will come can all become part of this cycle. A 2026 analysis of a randomized trial involving 290 adults with chronic insomnia found that digital cognitive behavioral therapy for insomnia, or CBT-I, was associated at three months particularly with reductions in sleep-related worry, dissatisfaction with sleep and difficulty relaxing. Other improvements appeared to spread indirectly through these core arousal-related changes.
The idea is important because it changes the question. An exhausted person may not necessarily need to become even more tired. In some cases, the more useful target may be the brain that has remained too alert for too long.
Then Comes the Phone
When sleep does not come, many of us reach for the object beside the bed. It is tempting to reduce the problem to a familiar villain — blue light — but a smartphone is much more than a source of light. It is a conversation, a television, a newsstand, a workplace, a shopping mall and an almost limitless supply of new information.
A person who once might have become bored enough to fall asleep can now reach practically the entire world without lifting their head from the pillow. The body may be saying that the day is over, while the phone continues to tell the brain that something else is happening. For an already activated brain, that endless stream of novelty can make the transition from wakefulness to sleep even harder.
Your Bed Can Learn the Wrong Lesson
Another problem can develop when insomnia continues for weeks or months. Night after night, you lie awake in bed, scrolling, working, worrying and calculating how many hours of sleep remain. Gradually, the bed can become associated not only with sleep but also with frustration, alertness and effort.
This is one reason stimulus control is a central part of CBT-I. Rather than spending long periods awake in bed struggling to force sleep, the approach tries to rebuild the association between the bed and actual sleep. The basic idea is simple: go to bed when sleepy, and if you remain awake long enough to become frustrated, leave the bed for a quiet activity in dim light and return when drowsiness comes back. The goal is not to punish insomnia. It is to teach the brain again that the bed is primarily a place where sleep happens.

In 2026, Researchers Put Digital CBT-I Against Zolpidem
This year brought an especially interesting experiment. On August 18, 2026, researchers reported an exploratory randomized controlled trial directly comparing a five-week digital CBT-I program with zolpidem, one of the best-known prescription insomnia drugs. At week five, the digital CBT-I group reduced subjective sleep-onset latency by an average of 20.65 minutes, while the zolpidem 5 mg group improved by 22.42 minutes. The difference between the two groups was not statistically significant.
Five weeks after treatment ended, the digital CBT-I group showed a stronger trend toward sustained improvement. But that later difference also did not reach statistical significance. Just as importantly, this was a very small exploratory study, so it cannot establish that digital therapy is as good as, or better than, zolpidem for the general population. The researchers themselves called for larger confirmatory studies.
Still, the study raises a compelling question: what if part of the future of insomnia treatment is not simply finding a stronger sleeping pill, but teaching the brain how to sleep again?
The Evidence Is Larger Than One Small Study
That question does not rest on one trial. A 2026 model-based network meta-analysis examined 73 randomized controlled trials involving 14,465 participants and found a clear nonlinear relationship between the duration of digital CBT-I and improvement in insomnia severity. In the model, benefits tended to plateau beyond roughly 300 total treatment minutes, while approximately 250 minutes emerged as a promising treatment duration.
This does not mean that everyone needs precisely 250 minutes of treatment. It does show, however, how far digital CBT-I has moved beyond generic advice such as avoiding coffee or turning off the phone. Researchers are now studying its dose-response relationship much as they would other therapeutic interventions.
That distinction matters. Sleep hygiene and CBT-I are not the same thing. Sleep hygiene can support better sleep, but CBT-I addresses the behavioral and cognitive processes that may perpetuate chronic insomnia: spending excessive time awake in bed, fearing another bad night, trying too hard to sleep and developing patterns that reinforce wakefulness.
What About Sleeping Pills?
Prescription sleep medications, including zolpidem, can be appropriate and useful for some patients. The point is not that medication is “bad” and behavioral therapy is “good.” The more useful question is whether medication is being used at the right dose, for the right person, and whether the insomnia itself is also being treated.
A 2026 pilot study called the SEDATIVE trial explored exactly that combination. Participants who had been taking sleep medications for at least three months received pharmacist-led supervised deprescribing alongside clinician-supervised CBT-I. The study was small and primarily designed to test feasibility, so its results should not be generalized to everyone. But its underlying idea is important: reducing sleep medication and treating insomnia do not have to be separate projects.
Instead of simply removing a pill and hoping for the best, clinicians may be able to combine gradual medication reduction with strategies that help the brain rebuild healthier sleep patterns.
If You Take Zolpidem, Do Not Simply Cut the Dose Yourself
The FDA has warned that zolpidem can remain in the bloodstream the next morning at levels high enough to impair activities requiring full alertness, including driving, even when a person feels fully awake. For immediate-release zolpidem, the FDA lowered the recommended starting dose for women from 10 mg to 5 mg and recommends that clinicians consider the lower 5 mg dose for men as well. For extended-release zolpidem, the lower recommended dose is 6.25 mg.
But that does not mean someone currently prescribed 10 mg should simply cut the medication in half tonight. The FDA specifically advises people already taking 10 mg or 12.5 mg to continue the prescribed dose until they have spoken with a health professional about how to proceed safely. The useful question to bring to a clinician is not “Can I just stop?” but rather: “Am I taking the lowest effective dose, and could CBT-I eventually help me need less?”
What Can You Actually Do Tonight?
There are several practical changes that fit the same science. Try to keep your morning wake time reasonably consistent, even after a poor night, because the wake time helps anchor the body clock. Go to bed when you are genuinely sleepy rather than simply because the clock says it is bedtime, and avoid spending long periods awake in bed trying to force sleep.
If you are lying awake and becoming frustrated, get out of bed for a while, keep the environment dim and quiet, and return when sleepiness comes back. Move caffeine earlier in the day if you regularly use it late. Give your phone somewhere else to spend the night if possible, not because a single look at a screen automatically causes insomnia, but because an alert brain does not need an endless supply of stimulation at midnight.
Most importantly, if insomnia persists, ask specifically about CBT-I, rather than assuming that a few sleep-hygiene tips are the same thing. And if you use prescription sleep medication, do not suddenly stop it or design your own taper. Discuss the dose and any reduction strategy with the clinician who prescribed it.
The Strange Paradox of Sleep
Perhaps the cruelest thing about insomnia is that sleep is one of the few things in life that can become harder the more desperately we try to achieve it. We can force ourselves to exercise, work or eat, but we cannot simply order the brain to sleep.
That is what makes the current research so interesting. Scientists are not only asking which chemical can make a person sleep. They are increasingly asking what keeps an exhausted brain awake, and whether that brain can relearn how to let go.
The person staring at the ceiling at two in the morning may not need to become more tired. They may need something very different: a brain that finally understands that the day is over.
TENVER VIEW
Sleep should not become a nightly contest between you and your brain. The emerging science of insomnia suggests that sometimes the answer may be less about forcing sleep and more about removing the conditions that keep the brain awake.
You cannot command yourself to sleep. But you may be able to teach your brain that it no longer needs to keep trying to stay awake.
Sources
- U.S. National Center for Health Statistics, Short Sleep Duration and Sleep Difficulties Among Adults: United States, 2024, April 2026.
- Betz LT et al., Targeting hyperarousal to improve sleep: A network intervention analysis of a digital intervention for insomnia, Behaviour Research and Therapy, 2026.
- Efficacy and Safety of a Novel Digital Cognitive Behavioral Therapy for Insomnia Application versus Zolpidem: An Exploratory Randomized Controlled Trial, Sleep Medicine, online Aug. 18, 2026.
- Defining the dose-response curve of digital CBT for insomnia, 73 RCTs, 14,465 participants, 2026.
- Bramoweth AD et al., SEDATIVE trial — Reducing sleep medication via parallel delivery of clinical pharmacist-led deprescribing and clinician-supervised asynchronous CBT for insomnia, Journal of Behavioral Medicine, 2026.
- U.S. Food and Drug Administration, Questions and Answers: Risk of Next-Morning Impairment After Use of Insomnia Drugs; FDA Requires Lower Recommended Doses for Certain Drugs Containing Zolpidem.
Medical note: This article is for general information only and does not replace individualized medical care. Persistent insomnia can have multiple causes, and prescription sleep medication should not be started, stopped or changed without appropriate medical guidance.
-

Does Chronic Stress Feed Cancer?
Scientists are uncovering a disturbing biological connection between chronic stress, the immune system, and the way cancer grows and spreads.

Most of us have heard some version of the phrase, “Stress is the root of all illness.” For decades, it sounded more like folk wisdom than hard science. Yet many of us have seen something unsettling: a person who seemed perfectly healthy goes through months or years of severe stress — the loss of a loved one, financial trouble, family conflict or overwhelming work pressure — and sometime later is diagnosed with cancer.
It is almost impossible not to wonder: Could the stress have had something to do with it? Science cannot answer that question with a simple yes. But researchers are beginning to uncover something potentially just as important.
First, Let’s Get One Thing Straight
There is currently no convincing evidence that psychological stress by itself turns a normal human cell into a cancer cell. Studies attempting to determine whether stressful life events increase the incidence of cancer have produced inconsistent results. The U.S. National Cancer Institute therefore remains cautious: the evidence that chronic stress directly causes cancer in humans remains unclear.
But scientists are increasingly asking a different question. What if cancer cells already exist? Could chronic stress change the biological environment around those cells in ways that make it easier for them to survive, grow or spread? Here, the science becomes considerably more interesting.
Stress Is Not Just a Feeling
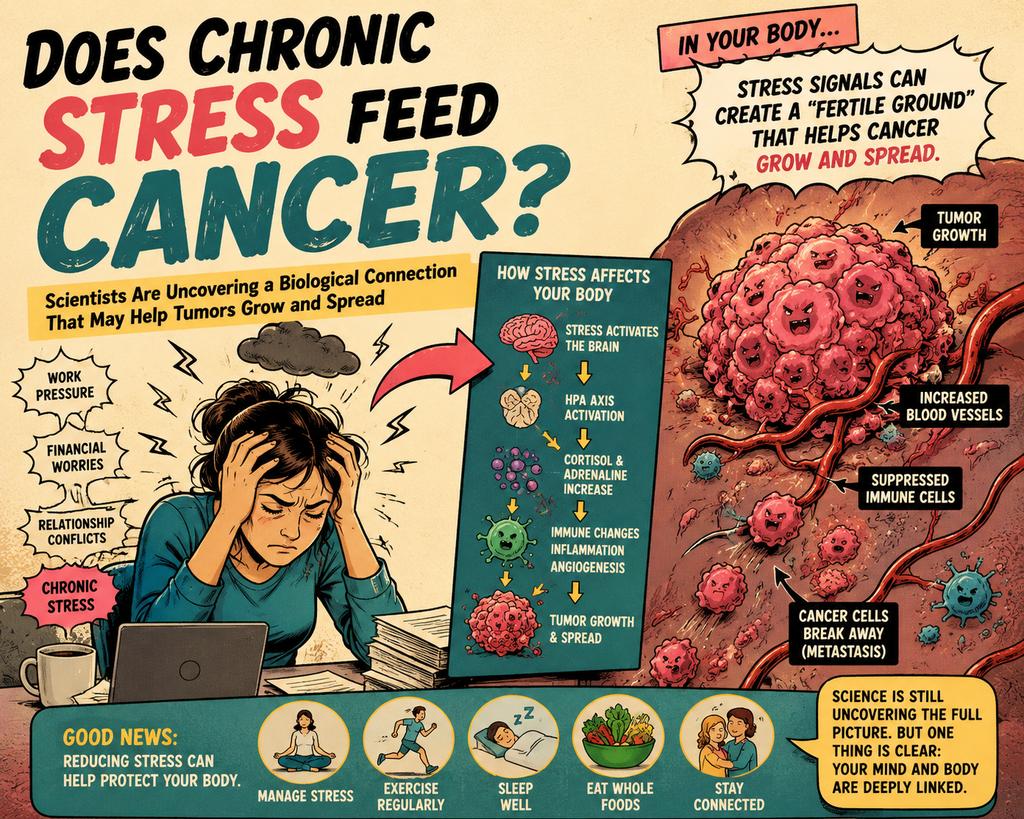
Stress begins in the brain, but it does not stay there. When the brain perceives danger or prolonged psychological pressure, it activates the sympathetic nervous system and the hypothalamic-pituitary-adrenal, or HPA, axis. This results in stress-related chemical signals traveling throughout the body, including adrenaline, norepinephrine and glucocorticoids such as cortisol.
For a short period, this response is useful. It prepares the body to react to danger by mobilizing energy and altering cardiovascular and immune activity. Chronic stress is different. When these signaling systems are activated repeatedly for weeks, months or years, their effects can reach immune cells, blood vessels and tissues throughout the body. Cancer researchers have discovered that tumors may respond to this altered biological environment.
A Tumor Does Not Live Alone
One of the major changes in modern cancer science is the realization that a tumor is not simply a collection of malignant cells. It exists within an entire biological neighborhood known as the tumor microenvironment, containing blood vessels, immune cells, connective tissue, signaling molecules and many other cells. Some components attack the tumor; others can unintentionally help it survive.
Laboratory studies suggest that stress-related signaling can influence inflammation, immune surveillance, blood-vessel formation and mechanisms involved in metastasis. The National Cancer Institute notes that studies in animal models and human cancer cells suggest chronic stress may promote cancer progression and spread.
That leads to an important distinction: Stress may not have to create cancer to influence what happens to cancer that is already there.
Then Came a Remarkable Experiment
In 2024, researchers published an unusually revealing study in Cancer Cell. Using mouse models of breast cancer, they found that chronic stress was associated with a striking increase in lung metastasis — approximately two- to fourfold. Instead of stopping at that observation, however, the researchers followed the biological trail to understand why.
Their investigation led to neutrophils, white blood cells that normally help defend the body against infection. Under chronic stress, glucocorticoid signaling altered these cells, causing increased formation of structures known as neutrophil extracellular traps, or NETs. NETs are sticky, web-like structures normally used to trap microorganisms.
In the stressed animals, however, NETs appeared to change the environment in the lungs in a way that made it more hospitable to metastatic cancer cells. When researchers disrupted NET formation, the stress-associated increase in metastasis was reduced.
The experiment therefore suggested a plausible biological chain: chronic stress alters hormonal signaling; hormonal signaling changes immune-cell behavior; those immune cells alter distant tissue; and that altered environment can make metastasis easier. This was principally an animal experiment and does not prove the same chain occurs in humans. But it demonstrated that stress can produce measurable biological changes capable of influencing cancer behavior in a living organism.
And in 2026, the Story Became Even Stranger
In 2026, another Cancer Cell study pushed the story into unexpected territory by identifying a possible connection among chronic stress, the gut microbiome, bacteriophages, immune responses and tumors. In mouse models of colorectal cancer and melanoma, chronic stress altered the microbiota and promoted movement of Enterococcus gallinarum into tumors.
Inside the tumor, the researchers found that bacteriophage-related signals could affect cancer-associated fibroblasts and local glucocorticoid production, which in turn influenced anti-tumor B-cell responses. When researchers interfered with key components of the pathway, some of the tumor-promoting effects associated with chronic stress were reduced.
Much of this mechanistic work was performed in mice, and the complete pathway has not been demonstrated in human patients. Nevertheless, it illustrates how dramatically the scientific picture is changing. Researchers are no longer thinking only in terms of “brain and emotion.” They are investigating networks that potentially connect the brain, stress hormones, immune system, microbiome and tumor microenvironment. Cancer is increasingly being studied as a whole-body biological system.
Scientists Have Even Tried Blocking the Stress Signal
Perhaps the most intriguing clue comes from humans. Researchers asked whether interfering with part of the body’s stress-response system could produce measurable changes inside an actual human tumor. They chose propranolol, an inexpensive beta-blocker that has been used for decades for cardiovascular and other medical indications.
In a randomized, triple-blind Phase II study, 60 women with operable breast cancer received propranolol or placebo for seven days before surgery. Researchers then analyzed their tumors and found changes in gene-expression patterns associated with metastatic potential as well as changes in immune-cell infiltration in the propranolol group.
This does not mean propranolol has been shown to prevent metastasis, cancer recurrence or death. The trial was small and examined biological markers rather than long-term clinical outcomes. The investigators themselves concluded that larger trials would be needed to determine whether these biological changes translate into meaningful effects on recurrence or survival.
Still, the experiment is noteworthy for a different reason. Researchers interfered with one component of stress-related signaling in actual cancer patients, and measurable biology inside their tumors changed. That moves the discussion beyond the vague notion that stress simply makes people “feel unhealthy.”
So, Does Stress Cause Cancer?
Here we have to be precise. Science has not established chronic psychological stress as a direct cause of cancer in humans. The evidence is nowhere near the level that exists for established carcinogens such as tobacco smoke, ionizing radiation or certain cancer-causing infections.
But a different proposition has increasingly strong experimental support: chronic stress may create biological conditions that help some existing cancers survive, grow or spread. Laboratory evidence is substantial, animal studies are revealing increasingly detailed mechanisms, and human biological evidence is beginning to emerge. What remains missing is definitive evidence that reducing psychological stress itself prevents metastasis or extends survival in cancer patients.
That distinction is crucial. The scientific story is not “stress causes cancer.” It is that stress may alter the biological terrain in which an existing cancer operates.
Maybe We Have Been Asking the Wrong Question
For decades, the question has been: “Can stress give me cancer?” Perhaps the more scientifically useful question is now: “What does chronic stress do to the biological environment in which cancer lives?”
That question is beginning to produce tangible answers. Stress hormones can change. Immune-cell behavior can change. Inflammatory signaling and the tumor microenvironment can change. In experimental models, metastatic behavior can change. Researchers are now even uncovering possible connections involving microorganisms living elsewhere in the body.
None of this means that someone developed cancer because they worried too much, worked too hard or experienced tragedy. Nor should a cancer patient ever be blamed for failing to “control stress.” What the emerging science suggests is something much more interesting: the boundary between psychological stress and physical biology may be far less distinct than medicine once assumed.
The brain is part of the body. Stress hormones circulate through the body. Immune cells respond to those signals. And a tumor exists within that same biological system.
TENVER VIEWS
We are not ready to say that stress causes cancer. The evidence does not justify that conclusion.
But science is beginning to support a subtler — and potentially more important — possibility: cancer may be able to exploit some of the biological changes created by chronic stress. Researchers are now investigating those changes at the level of hormones, immune cells, the tumor microenvironment and even the microbiome.
Perhaps one day scientists will learn how to interrupt these pathways. If that happens, managing the biological consequences of chronic stress could eventually become more than a matter of emotional well-being; it could become part of the broader scientific conversation surrounding cancer treatment itself.
We are not there yet. But the trail is getting harder to ignore.
Sources & Further Reading
National Cancer Institute — Stress and Cancer
National Cancer Institute — Stress-Induced Immune Changes May Help Cancer Spread
Cancer Cell / PubMed — Chronic Stress and Metastasis Study
Cancer Cell / PubMed — 2026 Chronic Stress, Microbiome and Tumor Immunity Study
Clinical Cancer Research / PubMed — Phase II Propranolol Breast Cancer Trial
TENVER MEDICAL NOTE
This article reports on emerging scientific research. Current evidence does not establish chronic psychological stress as a cause of cancer in humans. The studies discussed here should not be interpreted as evidence that beta-blockers, stress reduction or any other intervention can prevent or treat cancer. Medical decisions should always be made with a qualified healthcare professional.
-

What If Baldness Isn’t Permanent?
Inside the Global Race — and the $120 Million Bet — to Wake Sleeping Hair Follicles
For generations, the logic of baldness seemed brutally simple: once the hair was gone, it was gone. You could slow the loss, disguise it, or transplant follicles from one part of the scalp to another. But growing substantial new hair from areas that had gone quiet remained one of dermatology’s most stubborn problems.
Now scientists are asking a very different question: What if some of those follicles are not dead at all? What if they are simply asleep?
That question has moved far beyond speculation. A line of research that began in laboratories at UCLA has produced an experimental drug called PP405, which has now completed a randomized Phase 2a human trial. Researchers elsewhere are simultaneously pursuing stem cells, extracellular vesicles and other regenerative approaches to hair loss.
And something else is beginning to move: money. In October 2025, Pelage Pharmaceuticals — the UCLA spinout developing PP405 — raised $120 million in Series B financing co-led by ARCH Venture Partners and GV, formerly Google Ventures. Investment is not scientific proof; venture capital has backed plenty of drugs that eventually failed. But when sophisticated biotech investors put $120 million behind a treatment after seeing early human data, it becomes another signal worth watching. Science is sending one signal. Money is sending another.
The Follicle May Not Be Dead
The story begins with an unusual observation about stem cells. Hair follicle stem cells are long-lived cells capable of generating hair repeatedly throughout life. Much of the time, however, these cells are quiet — a state scientists call quiescence. When a new hair cycle begins, they awaken and become active.
Researchers at UCLA began investigating what controls that switch. In a landmark 2017 study published in Nature Cell Biology, scientists led by William Lowry and Heather Christofk found that hair follicle stem cells use metabolism differently from many neighboring skin cells. In particular, the cells produced unusually high amounts of lactate.
When researchers genetically blocked lactate production in mice, follicle stem cells failed to activate normally. When they altered metabolism in the opposite direction — increasing lactate production by interfering with the mitochondrial pyruvate carrier, or MPC — the stem cells activated more rapidly and the hair cycle accelerated.
The implication was striking: the hair follicle might contain something resembling a metabolic switch. Instead of replacing a follicle, perhaps medicine could learn how to turn that switch back on.
From a UCLA Laboratory to PP405
UCLA eventually licensed technology arising from the research to Pelage Pharmaceuticals, founded by Lowry, Christofk and medicinal chemist Michael Jung. PP405 emerged from that scientific lineage.
PP405 is a topical small molecule designed to inhibit the mitochondrial pyruvate carrier, altering cellular metabolism in a way intended to reactivate dormant hair follicle stem cells. That makes it fundamentally different from the best-known existing approaches to pattern hair loss.
Finasteride acts primarily through the androgen pathway by reducing the conversion of testosterone to DHT. Minoxidil promotes hair growth through a different mechanism and can prolong the growth phase of existing follicles. Hair transplantation physically moves viable follicles from one part of the scalp to another.
PP405 is attempting something else: wake up follicles that are already there.
Then Came the Human Trial
This is where the story becomes much more interesting. PP405 has completed a randomized, multicenter, double-blind, vehicle-controlled Phase 2a trial in adults with androgenetic alopecia — the medical term for common pattern hair loss.
The official ClinicalTrials.gov record lists 78 participants. PP405 was administered as a 0.05% topical gel; the randomized, blinded portion involved 28 days of treatment, followed by an open-label extension for eligible participants. The study is now marked Completed.
That distinction matters. PP405 is no longer simply a compound associated with intriguing laboratory biology. It has been put on human scalps under controlled clinical-trial conditions.
The 31% Signal
The trial was designed primarily to evaluate safety and pharmacokinetics, not to establish definitive efficacy.
Pelage subsequently reported a result that caught the attention of the hair-loss research community. Among men with a higher degree of hair loss, the company reported that 31% of those receiving PP405 achieved more than a 20% increase in hair density by week eight.
In the placebo group, the reported figure was 0%.
There is another intriguing detail. Participants received randomized treatment for only four weeks. The week-eight measurement therefore came approximately four weeks after treatment had stopped.
But those numbers require an important qualification. The 31% figure does not mean that 31% of all 78 trial participants grew 20% more hair. It comes from a subgroup of men with more advanced hair loss. And the figure comes from Pelage’s reported topline results rather than a complete peer-reviewed publication of the Phase 2a efficacy dataset.
That distinction is essential. The signal is strong enough to deserve attention. It is not yet strong enough to declare victory.
But Was It Actually New Hair?
This may ultimately be the more important question. Making existing miniature hairs somewhat thicker would be useful, but it would not represent the biological revolution PP405 is supposed to deliver.
The real test is whether previously inactive follicular units can begin producing mature hair again. At the 2026 American Academy of Dermatology Annual Meeting, PP405 data were presented by Dr. Arash Mostaghimi, Vice Chair of Clinical Trials and Innovation at Brigham and Women’s Hospital and an associate professor at Harvard Medical School. Pelage reported new terminal hair growth from previously dormant follicular units.
“Terminal hair” matters. It refers to the thicker, mature hair that gives visible scalp coverage rather than the fine, almost invisible vellus hairs commonly associated with miniaturization.
If larger independent trials reproduce that finding, it would provide important evidence that PP405 is doing more than protecting hair that is already growing. It may be reactivating follicular units that had stopped producing visible hair.
That is precisely the hypothesis the original UCLA science predicted.

Follow the Money
Then came the $120 million. The October 2025 Series B financing was co-led by ARCH Venture Partners and GV, with Main Street Advisors, Visionary Ventures and YK Bioventures also participating.
The investors did more than write checks. GV’s Cathy Friedman became chair of Pelage’s board, while ARCH venture partner Richard Heyman joined the board. Pelage said the financing would help advance PP405 into larger late-stage development.
Money does not validate a drug. Phase 3 trials exist precisely because promising Phase 2 drugs sometimes fail when tested in larger and more diverse populations.
But capital can reveal where sophisticated investors believe the next major scientific opportunity may lie. In this case, they are betting not simply on another hair-growth lotion, but on a larger concept: regenerative treatment for hair loss.
This Is Bigger Than PP405
PP405 is not developing in isolation. Scientists around the world are exploring regenerative approaches involving stem cells, extracellular vesicles, conditioned media, stromal vascular fraction and other techniques intended to influence the biological machinery of the follicle itself.
A 2026 systematic review in Stem Cell Research & Therapy examined 20 clinical studies involving 724 patients receiving various regenerative treatments for androgenetic alopecia. Across several categories, researchers found signals of increased hair density or thickness.
But the review also exposed the weakness of the field: small trials, inconsistent treatment protocols, different measurement methods and insufficient long-term data. That combination — promising signals but incomplete evidence — describes much of regenerative hair medicine today.
Still, the direction of travel is notable. Scientists are increasingly asking a question fundamentally different from the one that dominated hair-loss treatment for decades: instead of merely slowing hair loss, can the biological machinery responsible for producing hair be repaired or reactivated?
The answer is not yet known. But increasingly, the question is being tested in humans rather than only in laboratories.
Could This Replace a Hair Transplant?
For someone considering a hair transplant, the obvious question is unavoidable: Should I wait?
For now, the scientific answer is: not yet.
Hair transplantation has decades of clinical experience behind it. Surgeons relocate viable follicles, usually from areas resistant to androgenetic hair loss, into thinning or bald regions. PP405, by contrast, has not yet demonstrated in a large Phase 3 trial that it can restore cosmetically meaningful hair across the broad population of men and women with pattern hair loss. It is investigational, not FDA approved, and not commercially available.
There is also a biological limit worth remembering. A follicle that is dormant or miniaturized is not necessarily the same thing as a follicle that has been irreversibly destroyed. A drug cannot wake a follicle that no longer exists.
But if researchers can reliably reactivate large numbers of dormant follicles, the calculation surrounding transplantation could eventually change.
Hair transplantation moves follicles. Regenerative medicine is trying to wake them up.
COULD YOU BE IN THE NEXT TRIAL?
Phase 2a: COMPLETED — enrollment closed
Participants: 78 adults with androgenetic alopecia
Treatment studied: PP405 0.05% topical gel
Next step: Further late-stage clinical development is planned.Interested in participating? Pelage provides a way for people to register their interest in future PP405 studies. Potential participants should confirm official trial locations, recruiting status and eligibility requirements before applying.
Check PP405 future-study information at Pelage Pharmaceuticals
Check the official PP405 study record at ClinicalTrials.gov
Tenver is not affiliated with Pelage Pharmaceuticals and does not recruit participants or determine eligibility for clinical trials. Participation and eligibility are determined by the study sponsor and investigators.
What Would Make This a Breakthrough?
Several milestones now matter. First, the Phase 2 findings need broader scientific scrutiny and confirmation. Second, substantially larger late-stage trials must reproduce the efficacy signal while establishing longer-term safety. Third, researchers need to determine how durable newly generated hair remains after treatment stops.
Perhaps most important, investigators must determine who responds. Why do some participants apparently respond strongly while others do not? Does age matter? How long a follicle has been dormant? Does the degree of miniaturization matter? What about sex, genetics or the stage of hair loss?
Those questions may ultimately determine whether PP405 becomes a broadly useful treatment or a therapy effective only for a subset of patients.
TENVER VIEWS
For decades, the hair-loss industry has largely offered three choices: slow the loss, camouflage it, or move hair from somewhere else.
Regenerative medicine proposes a fourth possibility: repair the biological system that stopped working.
PP405 may succeed. It may disappoint in larger trials. Another therapy being developed somewhere else may eventually prove superior. Science does not yet allow us to know which outcome will prevail.
But something important has already changed. The question researchers are asking is no longer simply, “How do we prevent more hair from disappearing?” Increasingly, it is: “Can we make a silent follicle work again?”
Ten years ago, that question belonged largely to the laboratory. Today it is being tested on human scalps, presented at major dermatology meetings and backed by nine figures of venture capital. Since this article was first published, PP405 has continued to move forward — we follow the latest developments here.
That does not mean the cure for baldness has arrived.
It means the race has become real.
Sources & Further Reading
Flores A, Schell J, Krall AS, et al. “Lactate dehydrogenase activity drives hair follicle stem cell activation.” Nature Cell Biology (2017). This is the foundational UCLA work on lactate metabolism and hair follicle stem-cell activation.
Nature Cell Biology — Original UCLA Research
ClinicalTrials.gov — NCT06393452. Official registry record for the randomized PP405 Phase 2a study in adults with androgenetic alopecia.
ClinicalTrials.gov — PP405 Phase 2a
Pelage Pharmaceuticals. Company reports and program information concerning PP405, including clinical development and future-study information. Company-reported efficacy data should be distinguished from independently peer-reviewed clinical results.
Pelage Pharmaceuticals — PP405 Program
Stem Cell Research & Therapy. Systematic review of regenerative approaches being investigated for androgenetic alopecia.
PP405 is investigational and is not FDA approved or commercially available. This article is for informational purposes only and does not constitute medical advice or a recommendation to participate in a clinical trial.
-

Before Memory Fades, the Blood May Know
A New Blood Test Signals a New Era in Alzheimer’s Detection
For generations, Alzheimer’s disease has carried a particularly cruel uncertainty. A person begins forgetting names. A familiar route suddenly seems unfamiliar. A word that once came effortlessly disappears in the middle of a sentence. Families notice these small changes and eventually confront a frightening question: Is this simply aging — or is something happening inside the brain?
Until recently, answering that question could lead to specialized neurological examinations, expensive PET brain scans, or a lumbar puncture to analyze cerebrospinal fluid. Now, something as ordinary as a blood draw may begin to change that journey.
On August 19, 2026, the U.S. Food and Drug Administration cleared Elecsys pTau217, a new blood test developed by Roche in collaboration with Eli Lilly. Roche announced the clearance on August 24. The test is designed to help physicians determine whether a patient has the amyloid brain pathology associated with Alzheimer’s disease. It marks another major step toward something scientists have pursued for decades: finding evidence of Alzheimer’s-related changes in the blood.
What Is pTau217?
Two proteins have long been central to Alzheimer’s research: amyloid beta and tau. Amyloid can accumulate between nerve cells as plaques, while abnormal forms of tau are associated with damaging changes inside neurons. One particular form of tau — phosphorylated tau 217, or pTau217 — has emerged as an especially powerful blood biomarker for Alzheimer’s-related brain pathology.
What makes this development remarkable is where scientists can now measure that signal. Instead of looking directly inside the brain with a PET scanner or obtaining cerebrospinal fluid through a lumbar puncture, researchers can detect pTau217 in blood. The Elecsys test measures pTau217 in plasma and uses that information to help determine whether Alzheimer’s-associated amyloid pathology is likely to be present.
The test reports results in three categories — positive, intermediate or negative — helping physicians determine whether additional evaluation may be necessary. It does not replace a physician’s diagnosis, but it could make the first stage of investigating cognitive decline substantially simpler.
How Good Is It?
The scientific evidence behind pTau217 is what makes this development particularly compelling. In a 2026 study published in Alzheimer’s & Dementia, researchers evaluated the Elecsys pTau217 assay using samples from 2,148 people across five clinical research cohorts. Participants included people with cognitive impairment as well as people who appeared cognitively unimpaired, and researchers compared their blood results with amyloid PET imaging, an established method for detecting amyloid pathology in the brain.
Among cognitively impaired participants, those whose PET scans showed amyloid pathology had substantially higher pTau217 concentrations than those whose scans did not. The same general pattern appeared even among cognitively unimpaired participants. In other words, researchers were seeing in the blood a molecular signal closely associated with what PET imaging was revealing in the brain.
That relationship is why pTau217 has attracted such intense scientific interest. The goal is not simply to invent another laboratory test, but to find a reliable biological signal that can help physicians determine who is likely to have Alzheimer’s-related pathology and who may need more specialized evaluation.
Why a Blood Test Could Change Everything
PET imaging is sophisticated and valuable, but it is expensive and not readily available everywhere. Cerebrospinal fluid testing can also provide important information, but obtaining it generally requires a lumbar puncture. A blood sample is different: it can be collected in an ordinary medical office or laboratory.
Roche says its new test is designed to operate on more than 4,500 existing cobas laboratory instruments in the United States. That matters because much of the infrastructure needed to perform the test already exists. If blood biomarkers become routinely incorporated into medical practice, assessment for Alzheimer’s could gradually move beyond specialized memory clinics and neurological centers. A conversation that once might have begun with a specialist could increasingly begin in a primary-care physician’s office.
The implications could be especially important in communities where access to PET imaging or major neurological centers is limited. A blood test cannot replace all of those resources, but it may help physicians decide much earlier which patients truly need them.
Why Earlier Detection Matters More Now
There was once an uncomfortable question surrounding early Alzheimer’s diagnosis: Why discover the disease early if medicine could do little to alter its course? That calculation is beginning to change.
New disease-modifying treatments targeting amyloid pathology have emerged, while additional therapies are being investigated. These treatments do not cure Alzheimer’s. Their benefits can be modest, and their risks require careful consideration. But they introduce an important new reality: if treatment has its greatest opportunity to help during the earlier stages of disease, then identifying Alzheimer’s-related pathology earlier becomes increasingly valuable.
Diagnosis and treatment are therefore beginning to move closer together. A blood test could become one of the bridges between them — not because the test itself treats the disease, but because it may help identify the disease process at a point when medical decisions can potentially matter more.
What This Test Cannot Tell You
There is an important caution. Elecsys pTau217 is not a stand-alone test that tells someone, “You have Alzheimer’s disease.” The FDA-cleared use is for people 55 and older who already have signs, symptoms or complaints of cognitive decline. It is not intended as a general screening test for healthy people who simply want to know whether they might develop dementia decades from now.
Nor does a positive result automatically mean that someone has dementia. The test helps determine the likelihood of amyloid pathology associated with Alzheimer’s disease. Physicians must interpret the result together with symptoms, medical history, cognitive assessment and, when appropriate, additional diagnostic testing. The test also has not been established for predicting whether a person will eventually develop dementia or for monitoring whether an Alzheimer’s treatment is working.
That distinction matters. This is powerful science — but it is not fortune-telling.
The Larger Revolution
Perhaps the most important part of this story is not this particular test, but the direction medicine is moving. For much of medical history, the living human brain has been extraordinarily difficult to examine. Doctors often had to infer what was happening inside it from behavior, memory tests and neurological symptoms. Then came sophisticated brain imaging. Now, molecules circulating in the bloodstream are beginning to reveal biological changes associated with what is happening inside the brain.
The latest Elecsys test is particularly notable because a single biomarker — pTau217 — can support both rule-in and rule-out assessment of amyloid pathology, using validated clinical cutoffs across primary and specialty care. It is part of a rapidly developing field of blood-based biomarkers that could eventually alter how physicians approach one of the most feared diseases of aging.
What once required a highly specialized diagnostic pathway may increasingly begin with something remarkably ordinary: a tube of blood.
Before Memory Fades
Alzheimer’s disease remains one of medicine’s most formidable challenges. A blood test does not cure it. It cannot restore a forgotten name, a lost memory or a familiar face that has become difficult to recognize. But it may shorten the painful period of uncertainty between the first troubling signs and an explanation.
And as treatments continue to advance, time itself may become increasingly valuable. Earlier knowledge may give physicians more time to evaluate treatment options, families more time to plan, and patients more opportunity to participate in decisions about their own future.
For decades, medicine often recognized Alzheimer’s by what a person had already lost. The emerging science of blood biomarkers points toward a different future: one in which we may be able to see the disease process earlier — while there is still more memory left to protect.
TENVER VIEWS
The real significance of this breakthrough is not that Alzheimer’s can suddenly be cured — it cannot. It is that medicine may be shifting the timeline of the disease. For decades, Alzheimer’s was largely recognized after memory had already begun to disappear. Blood biomarkers such as pTau217 raise the possibility of identifying the biological signs of the disease earlier, more simply, and far more widely than before. As treatments improve, those additional months or years could become increasingly valuable. The future of Alzheimer’s medicine may depend not only on finding better treatments, but on finding the disease while there is still more of the person left to protect.
Sources & Further Reading
Roche Diagnostics. FDA clearance information for Elecsys Phospho-Tau (217P) Plasma, August 24, 2026.
This article is for informational purposes only and does not constitute medical advice. Alzheimer’s disease and cognitive impairment should be evaluated by qualified healthcare professionals.
-

What If Cancer Treatment Became Personal?
For most of modern medicine, cancer treatment has followed a familiar model: identify the type of cancer, then choose the best available treatment for it. But cancer is not quite that simple. Two people can have melanoma, yet the mutations driving their tumors may be very different.
What if, instead of giving both patients essentially the same medicine, we could build part of the treatment specifically for each person’s cancer? That possibility just moved an important step closer to reality.
A Milestone for Personalized Cancer Therapy
On August 19, 2026, Moderna and Merck announced that their Phase 3 INTerpath-001 trial had succeeded. The study involved 1,137 patients with high-risk stage IIB–IV cutaneous melanoma whose tumors had been completely removed by surgery. Researchers compared Merck’s immunotherapy drug Keytruda alone with Keytruda plus intismeran autogene, also known as V940 or mRNA-4157—an individualized mRNA therapy manufactured specifically for each patient.
The combination significantly improved both recurrence-free survival and distant metastasis-free survival compared with Keytruda alone. That matters because Phase 3 is where many promising experimental treatments fail. This trial cleared that critical hurdle.
According to Moderna and Merck, this is the first positive Phase 3 trial of an individualized neoantigen therapy—and of an mRNA-based cancer therapy.
How Do You Make a Cancer Treatment for One Person?
The idea is remarkably elegant. Doctors begin with the patient’s own tumor. Scientists sequence it and search for mutations that produce abnormal proteins called neoantigens—molecular signatures that distinguish the cancer cells from normal cells.
From those mutations, they select targets unique to that patient’s cancer. Then they manufacture an mRNA therapy carrying instructions for those targets. Intismeran can encode as many as 34 tumor-specific neoantigens.

Once administered, the mRNA helps train the immune system to recognize those targets. In simplified terms, the message is:
This is what your cancer looks like.
Learn it. Remember it. Attack it.Keytruda plays a complementary role. It blocks PD-1, one of the mechanisms tumors can exploit to restrain immune cells. One treatment helps show the immune system what to attack. The other helps free it to attack.
The Earlier Results Were Already Striking
The Phase 3 announcement did not come out of nowhere. An earlier randomized Phase 2b study followed high-risk stage III–IV melanoma patients for a median of 60.3 months—about five years.
Compared with Keytruda alone, the personalized mRNA combination produced a: 49% reduction in the risk of recurrence or death and a 59% reduction in the risk of distant metastasis or death.
Those are relative risk reductions, not claims that 49% or 59% of patients were cured. That distinction matters. But five years of follow-up suggested that the benefit was durable—and the larger Phase 3 trial has now crossed another critical threshold.
Why This Could Be Bigger Than Melanoma
The most important part of this story may not ultimately be melanoma. It may be the platform. Medicine has been moving toward precision oncology for years: sequence a tumor, identify a mutation, and choose a drug that targets it.
Personalized mRNA therapy takes the concept further. Instead of merely asking:
Which existing medicine best matches this patient’s tumor?
we can begin asking:
Can we manufacture a treatment from the biological information contained in this patient’s tumor?
That is a very different idea. The medicine is no longer entirely mass-produced. Part of it becomes personal.
Moderna and Merck are already testing intismeran across multiple cancers, including melanoma, non-small cell lung cancer, bladder cancer and renal cell carcinoma. If the approach succeeds in several cancers, this melanoma trial could eventually be remembered as something much larger than a melanoma breakthrough. It could become an early milestone in the industrialization of personalized medicine itself.
Hope, Without Hype
There is also plenty we still don’t know. This is not a vaccine that healthy people can take to prevent cancer. It has not cured cancer. Intismeran remains investigational, and the companies have not yet released the detailed numerical results from the Phase 3 trial. They plan to present them at an upcoming international medical meeting and discuss regulatory filings with health authorities. We also don’t yet know whether the treatment will extend overall survival.
And personalization creates a practical challenge: every treatment must be designed and manufactured from an individual patient’s tumor. Sequencing, computational analysis, manufacturing, quality control and delivery all have to happen fast enough—and eventually cheaply enough—to make the approach practical on a large scale.
So this is not the end of the story. It may be the beginning.
The TENVER View
The breakthrough is not that we have cured cancer. We haven’t.
The breakthrough is that an idea once confined largely to experimental medicine has now succeeded in a large Phase 3 trial: Take the unique genetic fingerprint of one person’s cancer. Turn that information into mRNA. And use it to teach that person’s immune system what to fight.
For most of medical history, millions of patients have been treated with medicines manufactured identically for millions of people. Cancer may be pushing medicine toward something different.
The question is no longer simply:
Can personalized mRNA cancer therapy work?
Now we can begin asking:
How well can it work?
For how many cancers?
How quickly can we make it?
And how personal can medicine ultimately become?Perhaps the future of cancer treatment will not be defined by finding one miraculous drug that defeats every cancer. Perhaps it will be defined by something almost opposite:
The age of treating “cancer” may slowly be giving way to the age of treating your cancer.
Key Papers & Sources
1. Moderna & Merck — INTerpath-001 Phase 3 Results (2026)
Phase 3 trial of intismeran autogene (V940) plus KEYTRUDA in high-risk melanoma
The Phase 3 trial met its primary endpoint of recurrence-free survival and its key secondary endpoint of distant metastasis-free survival.Merck — Phase 3 INTerpath-001 Results
2. Weber JS, et al. (2024)
Individualised neoantigen therapy mRNA-4157 (V940) plus pembrolizumab versus pembrolizumab monotherapy in resected melanoma
The Lancet
This randomized Phase 2b trial provided the clinical foundation for the Phase 3 program and demonstrated improved recurrence-free survival with personalized mRNA therapy plus pembrolizumab.3. Moderna & Merck — Five-Year Follow-Up (2026)
Long-term follow-up of KEYNOTE-942 / mRNA-4157-P201
At approximately five years of follow-up, the combination showed a 49% reduction in the risk of recurrence or death and a 59% reduction in the risk of distant metastasis or death compared with KEYTRUDA alone. -

Can We Really Regrow Teeth?
For generations, losing an adult tooth has meant one thing: it is gone for good. That assumption may finally be facing a serious scientific challenge.
The idea did not begin with a futuristic dental device. It began with an unusual observation in biology: when a protein called USAG-1 is removed or blocked, the molecular signals involved in tooth development become stronger—and in animal experiments, additional teeth can form.
But the story did not begin in 2021. Fourteen years earlier, in 2007, researchers reported something remarkable: mice lacking USAG-1 developed extra teeth. A year later, researchers connected the phenomenon to two of the biological signaling systems that help govern tooth development—BMP and Wnt.
The crucial leap came in 2021, when researchers showed that an antibody could block USAG-1 and restore tooth formation in animal models—turning a genetic observation into a potential therapeutic strategy.
Think of USAG-1 as a biological brake. During tooth development, signals such as BMP help tell cells when and where teeth should form. USAG-1 helps restrain those signals. The researchers’ idea was surprisingly simple: instead of trying to build a tooth from scratch, what if they could temporarily release one of the body’s own brakes and allow a dormant tooth-forming program to restart?
That idea eventually led to a humanized antibody called TRG035. Rather than implanting an artificial tooth or engineering one outside the body, the experimental treatment is designed to neutralize USAG-1 and potentially allow a tooth that failed to develop to resume its natural developmental program.
So, can a person who loses a tooth simply receive an injection and grow a new one? Not yet. The first human study of TRG035 was designed primarily to test safety, not to prove that the drug can regrow lost teeth. And the treatment’s first intended target is much narrower: people born with missing teeth, a condition known as congenital tooth agenesis.
Why start with people who were born without certain teeth? Because in some forms of congenital tooth agenesis, the biological machinery for making a tooth may not be entirely absent—it may have started and then stalled. Researchers describe these as developmentally arrested tooth germs. By blocking USAG-1, they hope to release that developmental brake and allow some of those tooth germs to continue growing.
Here is where the story becomes even more intriguing. Humans normally develop two sets of teeth—baby teeth and permanent teeth. But researchers have long observed evidence of what they call a “third dentition”: rudimentary tooth structures that can sometimes develop beyond the normal permanent set. In rare cases, these structures may help explain why some people develop extra, or supernumerary, teeth.
The Japanese researchers wondered whether this largely dormant third set could someday be deliberately awakened. In ferrets, whose two-stage dental pattern has similarities to ours, a USAG-1-neutralizing antibody produced an additional whole tooth resembling a third dentition. That result was striking—but it was still an animal experiment, not proof that the same thing will happen in humans.
Could This Eventually Replace Dental Implants?
Possibly—but that is a much bigger leap. Today’s dental implants replace a missing tooth with an artificial structure. Regenerative dentistry aims at something fundamentally different: persuading the body to produce a living tooth of its own. If that ever becomes reliable and controllable, it could transform dentistry. But TRG035 has not yet been shown to regenerate ordinary adult teeth lost to decay, gum disease, injury, or aging.
That distinction matters. A treatment that helps a developmentally arrested tooth grow is not the same as routinely replacing any tooth lost decades later. Researchers would still need to determine whether a new tooth can be generated in the right location, with the right shape and size, properly aligned with neighboring teeth, and safely integrated with bone, nerves, and the bite.
Where Things Stand Now
The program has completed its initial Phase I safety study in adults, which was designed primarily to evaluate the safety and dosing of TRG035—not to prove that people could grow new teeth.
The next test will be far more consequential. In August 2026, Japan’s PMDA completed its review of the clinical trial notification for a Phase IIa study of TRG035 in patients with congenital tooth agenesis, clearing an important regulatory step toward the next stage of clinical testing. The study must still proceed through the necessary institutional and clinical steps before it can provide the answer everyone ultimately cares about: can blocking USAG-1 actually restore missing teeth in people?
What We Know—and What We Don’t
What we know is genuinely exciting. Scientists have identified a biological pathway capable of influencing tooth formation, demonstrated tooth restoration or additional tooth formation in animal models, developed a humanized antibody targeting that pathway, and moved the treatment into human clinical development.
What we do not know is equally important. No peer-reviewed evidence has yet shown TRG035 growing a new tooth in a human being. We do not yet know how reliably a regenerated tooth could be positioned, shaped, controlled, or whether this approach will ever work for ordinary tooth loss later in life. Those questions remain open.
The TENVER View
Tooth regeneration is no longer merely a science-fiction idea. There is real biology behind it, years of animal research behind it, and now a drug candidate in human clinical development. That alone makes this a story worth watching.
But the most exciting possibility—the day when an ordinary adult could replace a lost tooth by growing a new one—remains a possibility, not a medical reality. The science has opened a door. It has not yet shown us what lies on the other side.
Key Papers & Sources
1. Murashima-Suginami A, et al. (2008)
Enhanced BMP signaling results in supernumerary tooth formation in USAG-1 deficient mouse
Biochemical and Biophysical Research Communications
An early study showing that mice lacking USAG-1 developed supernumerary teeth, helping establish USAG-1 as an important regulator of tooth formation.2. Murashima-Suginami A, et al. (2008)
Enhanced BMP signaling results in supernumerary tooth formation in USAG-1 deficient mouse
Biochemical and Biophysical Research Communications, 369(4), 1012–1016
This study showed that enhanced BMP signaling contributes to supernumerary tooth formation in USAG-1-deficient mice and helped clarify the signaling mechanism behind the earlier finding.3. Murashima-Suginami A, et al. (2021)
Anti–USAG-1 therapy for tooth regeneration through enhanced BMP signaling
Science Advances, 7(7), eabf1798
This landmark study showed that blocking USAG-1 with an antibody could rescue tooth agenesis in mouse models and induce whole-tooth formation. The researchers also demonstrated additional tooth formation resembling a third dentition in ferrets.4. Takahashi K, et al. (2024)
Development of a new antibody drug to treat congenital tooth agenesis
This paper describes the development of a humanized anti-USAG-1 antibody and the scientific path toward clinical treatment for congenital tooth agenesis.5. Toregem BioPharma Co., Ltd. (2026)
Announcement for Completion of the PMDA Investigation of CTN (Clinical Trial Notification) for TRG035 Phase IIa Trial
August 17, 2026
Toregem announced that Japan’s PMDA had completed the required investigation of the clinical trial notification for a Phase IIa study of TRG035 in patients with congenital tooth agenesis, clearing an important regulatory step toward the next stage of clinical testing.
NEW LIST TEST
-

जब एक व्यक्ति लौटता है, तो क्या होता है?
-
Che cosa accade quando una persona ritorna?
-
Was geschieht, wenn ein Mensch zurückkehrt?
-
Que se passe-t-il quand quelqu’un revient ?
-
一人の人間が帰ってきたとき、何が起こるのか
-
一个人回来之后,会发生什么
-
한 사람이 돌아오면 생기는 일
-
Lo que ocurre cuando una persona regresa
-
What Happens When One Person Comes Back
-
ยุคฟื้นฟูเกาหลี/
-
কোরীয় রেনেসাঁ
-
Renaisans Korea
-
Thời kỳ Phục hưng của Hàn Quốc
-
कोरियाई पुनर्जागरण
-
النهضة الكورية
-
Kore Rönesansı
-
O Renascimento Coreano
-
Корейский Ренессанс
-
Il Rinascimento coreano
-
El Renacimiento Coreano
-
韓国ルネサンス
-
韩国文艺复兴
-
La Renaissance coréenne
-
Die koreanische Renaissance
-
한국의 르네상스
-
The Korean Renaissance
-

What If Weight Loss Is Only the Beginning?
-

ଯେଉଁ ଆସନ୍ତାକାଲିକୁ ସେ ହୁଏତ ଦେଖିପାରିବେ ନାହିଁ, ସେହି ଆସନ୍ତାକାଲି ପାଇଁ ଗଛ ଲଗାଉଥିବା ମଣିଷ
-
The Man Who Planted for a Tomorrow He May Never See
-

When Normal Changes